Could MRI Reduce Prostate Biopsies?

Could MRI one day reduce the need to biopsy some patients with suspected prostate cancer before they get treatment? U.K. researchers raise that intriguing prospect in a new study in European Journal of Radiology. 

Biopsy is an integral part of the workup protocol for men suspected of having prostate cancer, typically due to their elevated PSA levels.

  • But prostate biopsy is an invasive procedure, and can cause both complications and anxiety in patients, as well as contribute to higher healthcare costs.

MRI has proven effective in selecting which patients should be sent for biopsy and which ones can be followed with active surveillance – thus avoiding biopsy’s negative consequences.

  • But what if you could eliminate biopsy altogether in some men by making the diagnosis directly with MRI, and sending patients straight to treatment? 

That’s what researchers from University College Hospital in London tried in the new EJR paper by studying 880 consecutive patients who presented to their prostate clinic and got multiparametric MRI scans. Of these, 251 were considered suspicious for disease based on their scans.

  • Radiologists interpreted the images, focusing specifically on cases where they were 99% certain that the suspected lesion was cancerous, but also grading cases at 90% and <90% certainty. Indeterminate cases could be forwarded to biopsy for further investigation.

Researchers discovered…

  • 79 patients (9% of the total) were in the “99% certain” category, with 69 going to biopsy – and 100% had clinically significant tumors.
  • 45 patients (5% of the total) were in the “90% certain” category, with 41 undergoing biopsy and 98% having clinically significant tumors.
  • The combined groups represented 14% of the patients presenting to the clinic and 49% of the suspicious cases, and only one individual did not have a clinically significant tumor.

Applying the findings to real-world clinical practice, patients in the “99% certain” or “90% certain” categories could be sent straight to prostatectomy, without the need for biopsy or PSMA-PET scans.

  • Such a straight-to-treatment protocol would be analogous to the treatment of kidney and testicular cancer, where patients are treated without biopsy on the basis of imaging scans that are definitive for cancer. 

The Takeaway

Previous studies have found that MRI can reduce biopsies in men with low suspicion of serious disease, instead directing them to active surveillance. The new research shows MRI also works at the other end of the spectrum, sparing men with clinically significant cancer the ordeal of undergoing biopsy before they can start their treatment.
VA Probes Radiologist ‘Mass Exodus’

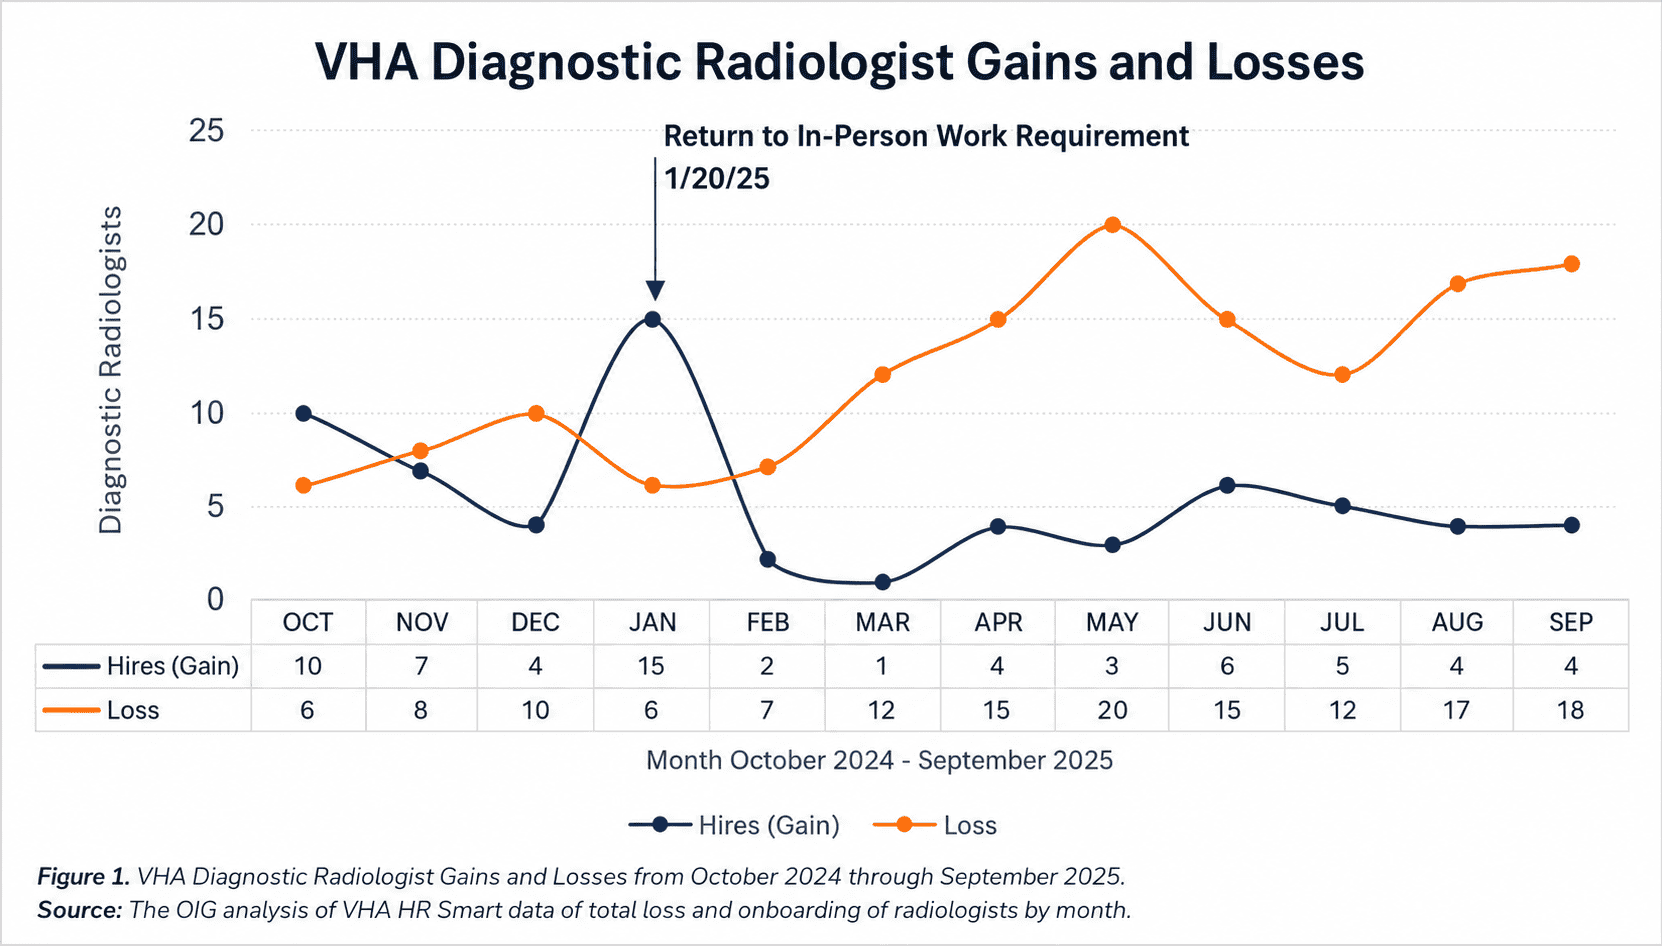
A new federal investigation confirms that a “mass exodus” of radiologists occurred at the VA hospital in Washington, DC, causing a backlog of imaging exams. The departures occurred in response to “return-to-office” requirements implemented in the early days of the second Trump administration. 

Reports began surfacing in late July of turmoil among VA radiologists that centered on the Washington DC VA Medical Center.

  • The departures were linked to changing federal policies on remote work, which has become commonplace in radiology.

The VA supported remote radiology work dating back to the COVID-19 pandemic under a policy that began as a temporary measure and subsequently “became standard practice” as radiologists were allowed to work from home several days a week. 

  • Indeed, teleradiology and remote radiology interpretations “have become factors in employment decisions for many radiologists, influencing recruitment and retention strategies across the industry,” noted a report issued in early August by the VA’s Office of Inspector General (OIG) investigating the turmoil. 

But all that changed on January 20, 2025, when a presidential memo was issued ordering heads of all federal departments and agencies to “take all necessary steps to terminate remote work arrangements and require employees to return to work in-person at their respective duty stations on a full-time basis.”

  • This sparked the departure of most of the Washington DC VA’s diagnostic radiologists, as four of the facility’s five full-time radiologists – including the chief of radiology – resigned over the next six months. 

The OIG report confirms that the return-to-office memo was a “tipping point” that “spooked” radiologists into leaving the Washington DC VA. 

  • While the VA later issued an exemption allowing remote work for radiologists, it wasn’t clear whether the exemption would be extended beyond one year, creating uncertainty and undermining the VA’s ability to recruit new radiologists. 

The turmoil has had several ramifications…

  • Body MRI scans were shut down in July 2025.
  • A backlog of CT exams developed in September 2025.
  • Imaging exams were sent out to community imaging centers.
  • The delays created the risk of patient harm, with the OIG report identifying six patient cases of particular concern.

The Takeaway

The new OIG report on radiologist departures from the VA provides a stunning look at the turmoil caused within one VA hospital by misguided government policies. The question is whether the facility’s challenges in retaining radiologists are just the tip of the iceberg, and whether similar problems extend throughout the VA health system.

CT vs. MRI for Pediatric TBI Surveillance

Sometimes less is more. That may be the case with pediatric CT for surveillance of traumatic brain injury, which should be limited as much as possible due to the radiation it delivers to young patients. Other modalities like MRI should be considered instead for follow-up.

That’s according to a new Viewpoint article in JAMA Pediatrics that proposes a new surveillance protocol relying on rapid MRI scans rather than CT to follow kids who have experienced TBI.

The authors note that the head is the most frequently imaged body region in pediatric CT, with a 2025 study claiming…

  • Cancer risk in scanned kids rose with higher radiation exposure.
  • Just two head CT scans added up to a 1.8X higher risk of hematologic malignancy by age 21.
  • 2-3 scans conferred a 2X higher brain cancer risk.

But regardless of how you interpret those statistics, few imaging specialists would dispute the need to keep pediatric CT radiation dose as low as reasonably achievable.

Instead of CT, the new imaging pathway proposed in JAMA Pediatrics recommends a rapid MRI protocol for surveillance imaging, as follows…

  • Initial TBI diagnosis should continue to be made with index cranial CT to identify hemorrhage. 
  • Stable patients should be referred to MRI using motion-tolerant and blood-sensitive sequences like T2 with gradient-echo or susceptibility-weighted imaging. 
  • Such sequences can be performed without sedation in 5-7 minutes or less.
  • For unstable patients, timely imaging – regardless of modality – and urgent neurosurgery consultation should be prioritized.  

But there are barriers to wider use of MRI, such as the availability of MRI scanners and technologists, especially outside daytime hours.

  • Nor do the authors recommend that children be transferred to other facilities solely to receive MRI scans. 

But in cases where MRI is available, every effort should be made to provide a radiation-free option for tracking children with TBI.

The Takeaway

Radiology has demonstrated impressive progress in reducing overall CT radiation dose in the long term. The new article recommending an MRI-forward pathway for following children with TBI shows that additional progress can be made when it comes to our most vulnerable patients.

CT Lung Screening Variation

Adoption of low-dose CT lung cancer screening is growing, and that’s a good thing. But rising LDCT utilization is also creating new challenges, illustrated by a new study in JACR that found high variability in radiologist interpretations. 

CT lung screening participation rates are rising, from single digits a decade ago to 19% in a recent survey. 

  • But there’s still a long way to go to get lung screening to the roughly 75% participation rate seen with breast cancer screening. 

One barrier to getting more people screened is false positives, which can cause patient anxiety and trigger a cascade of additional exams and procedures to work up suspicious findings. 

  • A major contributor to false positives may be variability in how radiologists read CT scans, so the JACR researchers investigated how interpretations for the same images changed between imaging specialists. 

Researchers looked at interpretations made by 1.4k radiologists, each of whom read a minimum of 50 LDCT screening exams (a total of 200k exams), then calculated false-positive rates for both baseline and follow-up exams. Researchers found…

  • High variability in false-positive rates, from 11% to 22%.
  • In random pairs of radiologists, on average, one radiologist would have twice the odds of making a false-positive call as the other. 
  • Radiologists with false-positive rates higher than the median rate also unsurprisingly had higher sensitivity than those below the median (97% vs. 92%).

What’s causing the variation? It could be because some radiologists use image interpretation patterns that increase false positives but also catch more cancers. 

  • In statistical terms, researchers found that for baseline screens read by radiologists who were below the median false-positive rate, they would have about 100 fewer false-positive screens for one fewer true-positive cancer. 

Radiologist variability could be reduced through programs to standardize screening interpretation, such as those implemented in mammography screening.

  • These could include support tools, automated feedback systems, educational interventions, and targeted double reading.

The Takeaway

The new findings on radiologist variability in reading CT lung cancer screening exams illustrate the delicate balance between detecting more cancer at the risk of producing additional false positives. Is the tradeoff worth it? We think we know how most patients would feel.

Rating CT Image Quality

As radiology strives to reduce CT radiation dose, one of its challenges is maintaining image quality while keeping dose low. A new five-star system for rating images is described in a new paper in EJR and could offer a solution by establishing an easy-to-understand global metric.

The radiology community has been making progress in reducing CT radiation dose, but much work remains to be done.

  • In particular, radiology professionals struggle between the desire for better-looking images – which usually result from higher radiation dose – with low-dose images that may be noisier but are good enough to make a diagnosis.

While there are lots of metrics for measuring radiation dose, image quality doesn’t have a widely recognized scale. 

  • So a team from the IAEA and MGH worked together to develop one, based on the widely recognized five-star paradigm for ranking consumer-facing businesses. 

In an interesting wrinkle, the five-star system acknowledges the dose dilemma, essentially penalizing images in which too much radiation dose was used to produce an image that’s crisper than what’s needed for diagnosis. 

  • On the other hand, the system rewards images that might be noisy due to use of less radiation, but that are still diagnostic.

 The system’s ratings are as follows…

  • Five stars – Acceptable, despite high image noise associated with low-dose CT.
  • Four stars – Acceptable for all parts within the region of interest.
  • Three stars – Acceptable, despite unintended high noise and/or some artifacts.
  • Two stars – Excellent quality with unjustifiably low image noise and no artifacts.
  • One star – Non-diagnostic, due to excessive noise or artifacts, or poor contrast.

To test the rating scale, IAEA and MGH researchers performed a study at six hospitals across five European countries. 

  • CT scans of 2.7k adults were acquired, and three radiologists per hospital were trained in the five-star scale and scored the images to see how reader subjectivity affected the scoring. 

The study found… 

  • Reader concordance was up to 93% at some sites, indicating little variability in scoring.
  • Overall discordance was rare, at 1.6%.
  • The two-star ratings (in which too much radiation was used) were associated with higher radiation dose in nearly all patient weight groups. 

The Takeaway

The new study shows that a five-star system for rating CT image quality is feasible and can reveal cases of unnecessarily high radiation dose. The question is whether the system remains an interesting thought experiment, or if it becomes an integral part of radiology’s effort to better manage radiation.

Could MRI Move the Needle in Prostate Cancer Workup?

Traditional systematic biopsy can miss clinically significant prostate cancers and often causes discomfort for patients along the way. While many countries have added MRI to prostate cancer workup protocols to determine which patients really need the needle, pre-biopsy MRI is used in only about one-third of U.S. prostate cancer workups – why?

More organized prostate cancer screening programs are popping up across the world. But a big challenge remains: deciding which patients with elevated PSA tests should undergo biopsy, and which ones can avoid or defer biopsy. That’s where MRI comes in…

  • ​​Australia, Canada, the U.K., and much of Europe have all adopted pre-biopsy MRI scans as the standard of care.
  • Pre-biopsy MRI scans are noninvasive and much more sensitive than traditional systematic biopsies, which typically obtain 10-12 cores to find lesions (93% vs. 50%).
  • The pace of MRI adoption for prostate cancer workup reflects ongoing disparities, with Black patients, people living outside cities, and Medicaid-eligible populations less likely to have access.

So, what’s the holdup in the U.S.? A new STAT article broke it down, finding:

  • Many U.S. urologists haven’t been trained in using MRI findings and/or performing MRI-targeted biopsy.
  • MRI access is still an issue across the country, especially in rural areas.

But something else may factor in: money. 

  • Biopsies can often be done in-house, so each procedure could mean up to $1.5k in reimbursement. 
  • Biopsies can detect low-grade cancers that might never become clinically significant, potentially leading to additional surveillance and repeat biopsies, which also generate revenue. 
  • Greater MRI use could reduce biopsy-related revenue.

Still, some organizations say yes to pre-biopsy scans, including the National Comprehensive Cancer Network, the American Urological Association, and the American Society of Clinical Oncology (albeit conditionally for the latter two).

  • Plus, a 2020 paper won over insurance companies to cover prostate MRI — but not all clinicians know that.
  • MRI scans have also proved helpful in other areas, like staging prostate cancer.

What could move the needle?

  • Training, ideally in urology residency, to overcome the knowledge gap early.
  • Education aimed at urologists and patients about reimbursement options and clinical benefits.
  • Improved access to high-quality MRI across the U.S.
  • Unified, implementation-focused programs like the one trialed in the Czech Republic, which led to a 10-percentage-point increase in pre-biopsy MRI utilization.

The Takeaway

The STAT article shows the U.S. is lagging far behind other countries in using MRI to diagnose and manage prostate cancer with more precision. Even though some major medical organizations are on board, broader implementation of MRI for patient workup requires overcoming limited training, barriers to technology access, and financial incentives that may favor biopsy.

Radiology Report Turnaround Slows

Radiologists are taking longer to interpret medical images than they did 10 years ago … and it’s a problem that appears to be getting worse. New data from the ACR’s Neiman HPI group, published in JACR, show that report turnaround times rose 27% between 2023 and 2024.

Report turnaround time (commonly referred to as TAT) is a closely watched barometer of radiologist productivity, and longer TAT could indicate radiologists are struggling to keep up with growing imaging volumes.

  • Another Neiman HPI study on TAT released earlier this year discovered a “hockey stick” effect, with turnaround times jumping sharply starting in 2022. 

But that study only tracked TAT through 2023. Meanwhile, anecdotal reports have surfaced of a “rapid increase” in turnaround times in late 2024.

  • So the updated research adds more recent data, analyzing newly available Medicare fee-for-service claims from 2024.

Researchers analyzed data from 2.9M office and hospital outpatient claims from 2014 to 2024, finding that TAT…

  • Grew just 14% in seven years from 2014 to 2021 (0.091 to 0.104 days).
  • But then rose at double-digit annual rates in 2023 (60%) and 2024 (27%).
  • Reached 0.251 days by the end of 2024, a 177% increase over 10 years. 
  • Increased at different rates by modality over the 10-year period, including CT (381%), MRI (278%), ultrasound (267%), and X-ray (126%). 

Why did TAT growth decelerate in 2024 over the year before? The Neiman HPI authors weren’t sure, but they said practice leaders may have taken steps to meet higher demand, like moonlighting and reactivating retired staff.

  • But these aren’t long-term measures that can meet the mismatch between supply and demand, suggesting instead that “the radiology workforce may be operating at or near maximum capacity.”

The Takeaway

The new data on slower radiology report turnaround times confirm fears that radiologists are struggling under rising imaging volumes and a stagnant workforce. While slower TAT growth in 2024 is a bit of a silver lining, it does little to hide the growing storm clouds on the horizon.

Rads Flee VA After Agency Banned Remote Work

A new report claims that radiologists fled the U.S. Department of Veterans Affairs health system after the agency eliminated policies allowing remote work in 2025. While the VA has since rescinded the ban, the article in The American Prospect claims that plummeting morale continues to plague the health system’s radiologists.

The VA’s Veterans Health Administration operates one of the largest health systems in the U.S., serving some 9.1M veterans through 170 VA medical centers and affiliated outpatient sites across the country.

  • While there are no official figures, estimates suggest the VA employs at least 1.5k radiologists, or 4%-5% of all active U.S. radiologists.

While radiologist salaries at the VA don’t approach levels found in the private healthcare sector, many imaging specialists are drawn to the system thanks to perceptions that it offers more job security and stability, as well as its mission in serving the nation’s veterans.

  • But the VA’s image of stability began changing in January 2025, the article claims, when the Trump Administration ordered federal employees to return to working in offices.

The order hit VA radiology particularly hard. Thanks to PACS and teleradiology, remote image interpretation has become a staple of the average radiologist’s workday.

  • Remote reading is even seen as a possible solution to radiology’s rising imaging volume and stagnant workforce. 

So it’s no surprise that VA radiologists recoiled against the new policy, which “ignored the realities of radiology work” and caused morale to plummet among the health system’s imaging specialists.

  • The VA eventually recognized its mistake and rescinded the in-office requirement for radiologists. But by then the damage was done. 

The article claims that VA radiology has experienced ongoing repercussions from the turmoil…

  • Many radiologists have left for the private sector, where average salaries are over 40% higher. 
  • Workloads for the remaining VA radiologists have skyrocketed.
  • Primary care physicians are reporting it now takes “days, not hours,” to get imaging results.
  • VA medical centers are being forced to outsource some specialized scans like amyloid PET exams, for which turnaround times are stretching to two or three months.

The Takeaway

It’s hard to tell exactly how many radiologists have left the VA health system, but any job loss is significant for a provider with a mission as important as the VA’s. While the agency’s turnaround on remote work is welcome, it’s likely that the country’s veterans will bear the brunt of the VA’s misguided policy change for years to come.

CT Radiation Dose Drops in Nationwide Survey

Some good news arrived this week in the campaign to reduce CT radiation dose. A new nationwide survey in Radiology found that radiation dose from CT scans has fallen markedly over the past decade in the U.S.

CT has been radiology’s workhorse modality since the 1980s thanks to its winning combination of cost-effectiveness and diagnostic power. 

  • But radiation dose has always been the modality’s Achilles heel. That was highlighted by a controversial 2025 paper claiming that routine CT could cause over 100k cancers in a year in the U.S.

There are plenty of technologies that effectively reduce CT radiation dose, but the trick has always been getting clinicians to use them. 

  • Another problem is standardizing best-practice CT protocols, so there’s less variation in radiation dose between CT scanners in the same health system or institution. The key to standardization is establishing best-practice benchmarks.

A landmark study published almost 10 years ago got the ball rolling by tracking radiation dose in 2014, producing key metrics like diagnostic reference levels (DRLs) and achievable doses (AD) for 1.3M exams at 583 U.S. CT sites.

  • DRLs represent the 75th percentile of dose distribution, while ADs are set at the 50th percentile, and both numbers represent targets for dose optimization efforts that are dynamic and can change over time. 

In the current study, researchers updated the radiation knowledge base with new data from 5.2M CT exams at 592 U.S. facilities, a 4X larger sample than in 2014, finding…

  • Overall radiation dose fell by 22% as measured by volume CT dose index (CTDIvol) and by 20% using dose-length product, another common radiation measure.
  • The largest dose reductions came in chest CT with contrast (-31%) and chest CT without contrast (-27%), while head CT without contrast fell 3.5%. 
  • New levels of achievable dose benchmarks were set for a variety of CT exams, giving CT facilities new targets for radiation dose reduction that are in some cases as much as 19% lower than 2014 targets.

The Takeaway

The new findings on CT radiation dose reduction are a welcome counter to recent studies that have whipped up hysteria around medical radiation. But now is no time to take the foot off the pedal – radiology must continue to drive dose lower through a combination of new technologies and judicious protocol standardization.

AI Closes Mammo Gap Between Generalists, Specialists

Mammography screening exams are some of the most challenging medical images to interpret, but due to staffing issues many mammograms are read by general radiologists rather than specialists. A new study in Radiology found that an AI-based workflow helped close the gap, leading to a 25% improvement in the cancer detection rate for general radiologists.  

Most of the big population-based studies on mammography AI have been conducted in Europe, where breast screening is performed under a double-reader paradigm that has two radiologists interpreting exams.

  • In this scenario, studies have shown that AI can eliminate the need for a second reader, cutting workforce requirements with the same or even better cancer detection rates.

But U.S. breast screening programs don’t use double-reading, leaving many to wonder where AI fits into the single-reader paradigm – especially when that reader is a general radiologist with no breast fellowship training. 

  • The new study offers some clarity. Researchers developed an AI-based workflow that integrated DeepHealth’s ProFound Pro 2.x deep-learning application into DBT-based screening programs. 

They set up AI as a “safeguard review.” After a radiologist’s initial interpretation, AI analyzed non-recalled mammograms for suspicion of cancer. Exams that exceeded ProFound’s risk threshold were flagged and routed to an expert reviewer.

  • If the reviewer agreed with AI, the original interpreting radiologist was consulted and had final authority on whether to recall the case. 

The safeguard review concept was tested at 109 breast imaging facilities that saw 578k DBT mammography exams from 2021 to 2022. In particular, researchers focused on the impact the safeguard review had on interpretation accuracy of both specialists and general radiologists, finding…

  • The cancer detection rate of generalists improved 25%, from 3.76 to 4.99 cancers per 1k exams.
  • The CDR of specialists did not change at a statistically significant level (from 4.47 to 4.76, p = 0.33).
  • There was no statistically significant difference between AI-aided generalists and specialists.
  • Generalists became more efficient at cancer detection, as evidenced by 15% improvement in their positive predictive value (from 3.38% to 3.89%). 
  • Although generalists’ recall rates did increase with AI (from 9.06% to 10.4%). 

The Takeaway

The new study offers an intriguing look at how AI can be integrated into U.S. breast screening programs without dramatically disturbing workflow. It also shows how diagnostic performance can be improved in an environment where general radiologists are being asked to fly solo in an area they didn’t train in.

Get every issue of The Imaging Wire, delivered right to your inbox.