Radiology AI Has an ROI Problem

Three out of four organizations using imaging AI cannot demonstrate a quantified positive return. The mistake may begin with what the CIO in radiology buys first.

Radiology has spent years asking whether AI works. It now has a harder question: who can prove it pays? 

In Black Book Research‘s December report, based on responses from 212 imaging leaders, only 24% of organizations using AI could report a quantified positive financial return. The rest might have benefited. They couldn’t show it.

The temptation is to respond with longer pilots, more committees, and another signature. But an additional approval gate cannot repair a purchase whose financial benefit was never aligned with the buyer.

Consider detection and triage. The algorithm can be clinically valuable, even lifesaving. 

But a faster stroke response may save resources in neurology or emergency care while radiology pays for deployment and integration. That is a real benefit with a misplaced ledger entry. Clinical value and departmental ROI should not be confused.

The first MRI AI investment should pass two tests. Can it generate measurable improvement in the imaging operation? And can it work across the entire fleet – from aging magnets to newer scanners already using OEM AI?

Vendor-neutral image enhancement offers one answer. By improving accelerated scans across makes and generations, it can create usable capacity without buying a new scanner. 

But that capacity only becomes revenue if schedules, staffing, and referral volumes let departments fill new appointments. Count completed exams, overtime, wait times, and avoided capital costs – not theoretical minutes saved.

At 3T Radiology & Research, exam volume rose 42% in the first two months after deployment of SwiftMR from AIRS Medical, generating $205,567 in reported incremental revenue.

SimonMed took that logic enterprise-wide: over 200 MRI scanners, different manufacturers, generations and field strengths, deployed in 10 days. 

The objective wasn’t to improve one scanner. It was to bring an entire mixed fleet under a common performance strategy.

That decision also creates a foundation for what comes next. An image is the input for every clinical AI tool, whether it detects, quantifies, or segments. 

If scanner-to-scanner differences affect noise, contrast, and sharpness, they can also affect those outputs and the longitudinal comparisons built on them. 

Establishing more consistent images across the network gives those tools a stronger starting point, with reproducibility validated rather than assumed. 

The Takeaway

Radiology doesn’t need to abandon diagnostic AI. It needs a purchasing sequence tied to who benefits, what can scale, and how outcomes are audited. Start with the MRI infrastructure you own. Measure the operational return. Then build the intelligence.

Jina Park is Chief Strategy Officer at AIRS Medical, maker of SwiftMR, an FDA-cleared, vendor-neutral MRI image-enhancement solution compatible with scanners from multiple manufacturers at field strengths up to 3T.

Source: Black Book Research, RSNA Imaging AI Flash Poll, December 4, 2025.

RadNet to Buy ONRAD in Teleradiology Shift

Consolidation in the teleradiology market picked up speed this week as outpatient imaging provider RadNet announced an agreement to buy ONRAD for up to $560M. The acquisition is big news in its own right, but it also shows how radiology’s workforce challenges are driving a restructuring of the imaging services segment.

RadNet announced on October 26 that it had agreed to acquire ONRAD from its private equity owner Housatonic Partners for $350M in cash and 5M shares, with an earnout clause worth up to $210M. The deal is expected to close in early 2027.

  • ONRAD has over 130 radiologists under contract who read imaging exams via teleradiology for more than 225 hospitals in 26 states. The company is expected to add $190M to $200M in annual revenue to RadNet.

ONRAD is based in Phoenix and itself has grown through acquisition in recent years, such as its purchase of Direct Radiology from Philips in late 2024. 

  • ONRAD already had a relationship with RadNet, as it was the first customer for DeepHealth OS, the AI operating system developed by RadNet’s DeepHealth subsidiary. 

In fact, it was that relationship that ultimately led to this week’s acquisition announcement. In an interview with The Imaging Wire, RadNet President and CEO Howard Berger, MD, said the company’s work with ONRAD gave it greater exposure to the rising volume and staffing challenges hospitals are facing. 

  • The radiologist shortage has been slowing down reporting times for hospital-based radiologists and even delaying patient diagnoses, prompting facilities to turn to teleradiology for help. 

RadNet is no stranger to teleradiology, using it extensively within its own network of outpatient imaging centers, Berger said. 

  • But with the ONRAD acquisition, RadNet will offer teleradiology to external customers, mainly hospitals that need extra interpretation capacity.

That will bring RadNet into more direct competition with radiology’s 800-pound gorilla, Radiology Partners. 

  • RP historically has focused on rolling up radiology groups rather than running outpatient imaging centers, but it does operate the vRad teleradiology business that competes directly with ONRAD, and in August RP announced an acquisition of international teleradiology provider Everlight. 

RP also has its own dedicated AI subsidiary, Mosaic Clinical Technologies, that markets AI algorithms that compete with those from RadNet’s DeepHealth.

  • In fact, it’s the AI angle that makes all of these recently announced acquisitions so intriguing.

While hospitals debate whether and how to adopt AI, imaging services providers have apparently decided to develop their own AI, offer it through their own provider network, and then build additional revenues through third-party sales.

  • It’s a philosophy that also seems to be driving Harrison.ai’s partnership with teleradiology provider Frontier Radiology (albeit on a far smaller scale).   

The Takeaway

RadNet’s planned acquisition of ONRAD reflects two separate but related trends in radiology – the ongoing workforce crisis and growing adoption of AI to try to solve it. The consolidation suggests that a broad restructuring of the U.S. radiology market is occurring that combines traditional imaging services with teleradiology, with a strong helping of AI to speed things along.

Better Lung Screening Strategies

In our last issue, we discussed how CT lung cancer screening is falling short, mostly because so many eligible people still aren’t getting screened. In this issue, we offer strategies for fixing the problem, based on studies published last week in JACR. 

A lung cancer diagnosis was once thought of as a death sentence, as it was usually diagnosed at a late stage.

  • But that dynamic has changed with low-dose CT screening, which detects cancers small enough to be effectively treated – as was the case with Pope Leo XIV earlier this month. 

But uptake of LDCT screening has been slow, with U.S. screening rates below 20% for eligible people – compared to nearly 80% for mammography. 

  • The new JACR articles include three studies that cover a range of relevant topics in screening, from boosting participation rates to ensuring quality in screening programs. 

In the first study, researchers described their LungCheck program for boosting LDCT rates. 

  • LungCheck focuses on outreach to primary care providers with educational materials and meetings that explain screening eligibility criteria, as well as patient navigators for follow-up and scheduling and EHR modifications to capture eligible people.

Across 5.9k people, LungCheck led to almost 3X higher odds of an eligible person getting LDCT screening at academic centers (OR = 2.67), and almost 5X at federally qualified health centers (OR = 4.53).

The second JACR study specifically addresses outreach to Hispanics, a traditionally underserved population for LDCT screening. 

  • Researchers analyzed the effectiveness of their Empower LCS program, which included a culturally adapted decision aid, provider notifications, and patient text reminders. 

While the sample size of 60 patients was small, there were significantly higher ordering rates for patients in Empower LCS at four months than usual care (50% vs. 13%), as well as more lung screening discussions (40% vs. 17%). 

  • There was a trend toward greater completion of LDCT screening exams, but the difference wasn’t statistically significant, probably due to the small sample size (30% vs. 13%, p = 0.117). 

In the third paper, researchers assessed how well the ACR’s Lung Cancer Screening Registry mapped to IASLC quality measures.

  • While 69% of IASLC measures mapped to registry data, 31% didn’t line up, especially data on patient entry, treatment, and wait times. 

The Takeaway

The new JACR studies show the promising advances being made to boost CT lung cancer screening participation, while also helping imaging facilities improve the quality of their service. All that’s left to do is to put these promising ideas into broader practice.

The Cost of Contrast Reactions

Everyone agrees that contrast media reactions are bad for patients. But contrast reactions also have an economic cost to imaging facilities, a cost that’s detailed in a new article in JACR. 

Patient contrast reactions are one of the main reasons why medical imaging isn’t always as noninvasive as everyone likes to think it is. 

  • Reactions can range from mild responses like skin rashes to more severe and even fatal episodes, like the case of a Brazilian woman who died after getting CT contrast in 2025. 

But contrast reactions can also be expensive for medical imaging facilities, even though they occur rarely (0.2% to 0.7% of scans, per published literature, with severe reactions far less common).  

  • To get a handle on these expenses, the Mayo Clinic’s Jennifer McDonald, PhD, and Robert McDonald, MD, PhD, tracked the costs involved in preventing and managing contrast reactions over five years at their institution. 

The McDonalds tracked 364k CT studies and 254k MRI exams that used contrast from 2019 to 2024 at Mayo Clinic, recording the number of physiologic or allergic-like patient reactions and the cost of medications and treatment for them, finding…

  • The reaction rate was slightly higher for CT compared to MRI (0.3% vs. 0.21%).
  • More CT cases than MRI required transfer to the emergency department (6.3% vs. 3.5%) or escalation to hospital care (2.1% vs. 0.2%).
  • Median costs per patient across the entire dataset were higher for CT than MRI ($15 vs. $1.66).
  • But severe reactions were expensive, with one CT case costing $238k for a nine-day hospital stay, while the most severe MRI case cost $7.4k for a one-day stay.
  • The amount of extra time required in the radiology department was similar between CT and MRI (25 and 27 minutes).
  • Two patients in the cohort died, but for reasons unrelated to contrast administration.

The authors then calculated the amount of extra work required in radiology to manage reactions, which they estimated came out to 13 additional hours in CT and 9.5 hours in MRI per 10k exams.

The Takeaway

Most radiology departments are doing a good job keeping contrast reactions to a minimum, while vendors are developing new agents with better safety profiles. The new study provides a useful benchmark against which imaging facilities can measure themselves.

Azra AI’s Blackford Plans

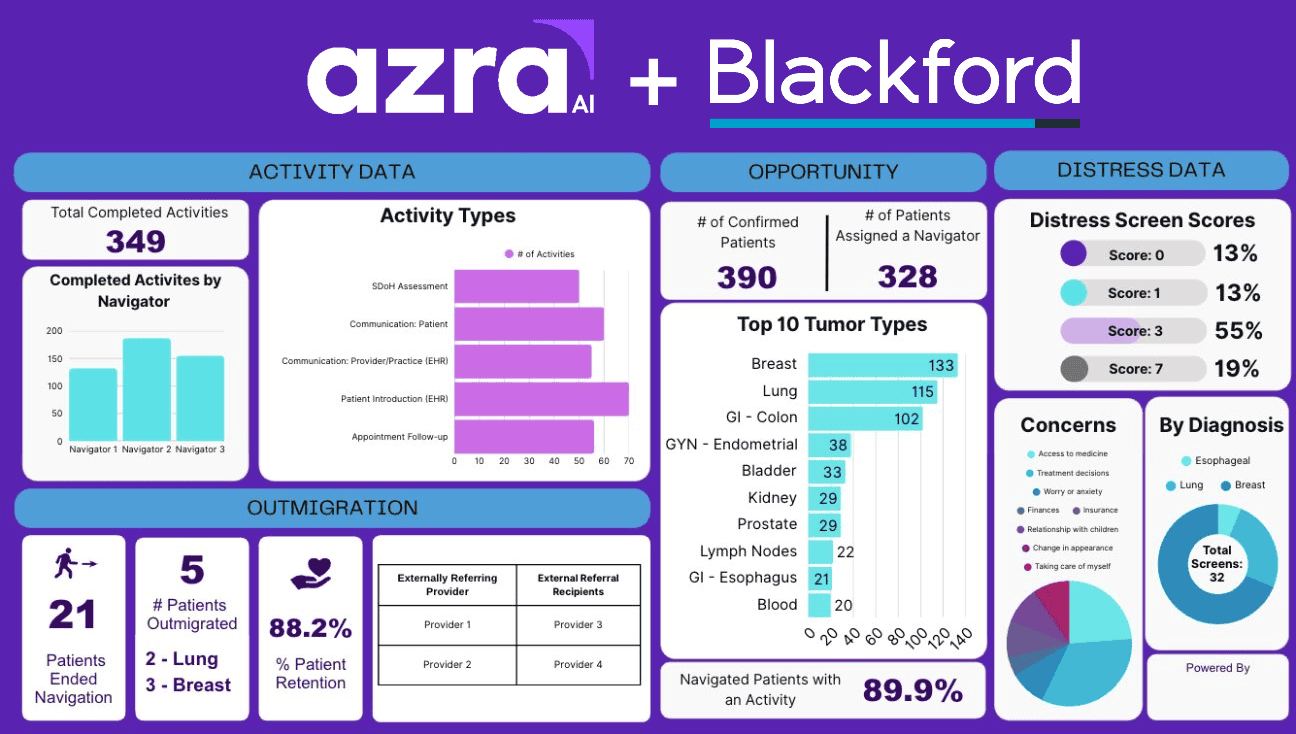
What are Azra AI’s plans for its new acquisition, AI platform company Blackford Analysis? Azra AI sees Blackford as a key piece in its effort to leverage artificial intelligence to ensure that patients with incidental findings or a cancer diagnosis don’t fall through healthcare’s cracks. 

Azra AI announced on October 9 that it would be merging with Blackford after Azra’s primary investor, private equity firm Sopris Capital, acquired the Scotland-based platform AI company. 

  • The announcement capped a year of uncertainty for Blackford that began in September 2025, when parent company Bayer announced it was stepping away from the digital platform business. 

In an interview with The Imaging Wire, Azra AI CEO John Marshall described the factors that attracted the company to Blackford…

  • A large stable of about 135 AI algorithm companies on Blackford Platform.
  • Strong relationships with OEM companies, for whom Blackford provides its AI orchestration platform on a white-label basis.
  • Contracts with major U.S. health systems, including the Veterans Health Administration. 

But who is Azra AI? The company offers solutions for one of the biggest challenges in healthcare – tracking patients with incidental findings or a diagnosis like cancer and managing their care. 

  • Azra AI emerged in 2022 after Sopris Capital funded the acquisition of healthcare assets from Digital Reasoning. The company got a major boost earlier this year when it acquired Thynk Health, which developed software for performing CT lung cancer screening and tracking incidental findings.

Marshall is a longtime imaging industry veteran (he attended his first RSNA at age 23) who took the helm at Azra AI in 2024, and since then revenues have grown 12X.

  • Patients with incidental findings or a cancer diagnosis are often lost to follow-up care, but Azra AI’s software helps bring them into an organized system where they can be followed and tracked. Where implemented, it has boosted patient retention rates for various conditions from 43%-69% to 90%-96%. 

One of the combination’s immediate advantages is synergy – patients flagged for a disease by a point-source algorithm on Blackford Platform can then be directed to Azra AI solutions for follow-up care. 

  • What’s more, Azra AI will now be able to sell its oncology tracking software to Blackford customers – both OEMs and healthcare providers.

Despite the turmoil of the past year, Marshall said Blackford’s team deserves praise for keeping the lights on and the servers humming. 

  • “The team that was there did a Herculean job,” he said. 

The Takeaway

Azra AI’s takeover of Blackford raises exciting prospects for the radiology AI sector, uniting point-source AI available through Blackford with Azra AI’s patient tracking expertise. It’s a synergy that looks set to leverage the power of AI for better patient care. 

Big Prostate AI Study Supports Screening Role

A new international study testing AI’s performance in analyzing prostate MRI exams could lay the groundwork for the technology’s broader role in prostate cancer screening. In the SCARLET-1 study in Radiology, researchers found that an open-source AI algorithm performed well – and consistently – across different research studies. 

Prostate cancer screening stands on the cusp of population-based adoption, but concerns remain about false positives, particularly how to determine which men should undergo biopsy and which ones can be directed to PSA monitoring. 

  • MRI has proven invaluable for working up patients with elevated PSA levels, but it’s expensive and requires a level of radiologist expertise that’s usually only available at high-volume centers. 

AI could help by automating key parts of the MRI process, enabling the modality to be offered more broadly to support prostate cancer screening.

  • The SCARLET-1 study investigated AI’s potential by combining results from research studies conducted in 22 countries around the world: PRIME, STHLM3-MRI, and IP1-PROSTAGRAM.

All three studies used an updated version of the PI-CAI AI algorithm, developed as part of a challenge sponsored by the Prostate Imaging-Cancer AI consortium in 2024.

  • In all, 2k patients received prostate MRI on 1.5T and 3T scanners, and the PI-CAI algorithm was used to analyze exams at different sensitivity and specificity thresholds to detect cases suspicious for prostate cancer rated at Gleason grade group ≥ 2, the threshold for clinically significant cancer. 

When compared to interpretations by local radiologists, prostate AI…

  • Achieved good AUC across the three studies (AUC = 0.84 to 0.89).
  • Had significantly higher agreement with an external reference standard than local radiologists (13 to 16 percentage points).
  • Maintained a positive net benefit across different thresholds, in particular those intended to reduce biopsies (patient must have > 30% chance of cancer).
  • Predictably, sensitivity thresholds affected AI’s performance, with higher sensitivity detecting more cancers but also generating more biopsies. 

The Takeaway

The SCARLET-1 study confirms that AI of prostate MRI performs as well as radiologists in real-world settings across multiple different locations. That’s important in making prostate cancer screening available in areas where specialty expertise may not be available to interpret imaging exams.

Blackford Finds Buyer with Sopris Acquisition

One of radiology’s longest-running mysteries was resolved late last week when a U.S. private equity firm acquired AI platform company Blackford Analysis from Bayer. Sopris Capital said it would fold Blackford into another radiology AI property it owns, Azra AI, as it builds its healthcare technology portfolio. 

The news comes just over a year after Bayer made the stunning announcement that it was backing away from the AI platform business and would “discontinue offerings and services” in the sector, including Blackford. 

  • The move reversed several years of Bayer’s investment in digital platforms, including the company’s own Calantic Digital Solutions division, which had been formed in 2022. 

The announcement left Blackford twisting in the wind. Some industry experts questioned the long-term viability of the AI platform model, in which platform companies act as middlemen between algorithm developers and end-users, adding a markup that made AI deployment more expensive. 

  • But others still see AI platforms and algorithm orchestration as a necessary foundation for successful AI deployment, especially given the explosion of clinical algorithms and the complexity of IT integration.

For its part, early reports following last year’s Bayer announcement suggested that Blackford’s business model was sound, with the company reporting a strong pipeline of prospective customers. 

  • And despite the departure of key executives like founder Ben Panter, Blackford continued operations under new managing director James Holroyd. The company even exhibited at SIIM 2026 – not exactly a sign of a firm about to go under. And not long after SIIM, Blackford announced a new partnership with Azra AI – perhaps a portent of last week’s announcement. 

So what do we know about Sopris? With its main offices in Colorado and Florida, Sopris first invested in Azra AI in 2022 to help the company acquire Digital Reasoning and expand into oncology. 

Sopris sees the Blackford acquisition as adding an AI orchestration capability to its growing imaging IT portfolio, combining Blackford with Azra AI. 

  • Blackford will remain a separate legal entity with operations in Scotland and the U.S., and will continue serving its existing OEM partners and health system customers “with no disruption to current deployments or operations.” 

The Takeaway

The Sopris acquisition of Blackford means that one of the radiology AI sector’s most established companies will continue operations for the foreseeable future. It also raises the intriguing prospect that a new player is entering the game to drive AI consolidation. 

How Common Are Imaging Deserts?

Amid concerns about equitable access to healthcare, questions have arisen about imaging deserts – U.S. regions without any access to radiology services. A new study in Academic Radiology probes the issue, finding that it may not be as bad as originally feared – for reasons unique to radiology. 

Uneven access to healthcare – particularly in rural regions – has become a common refrain in analyses of the U.S. healthcare system. 

  • In radiology, the issue has reached into the debate over workforce shortages as open jobs go unfilled in rural areas while urban positions are snapped up quickly – a trend one job board dubbed “geographic inconvenience.” 

But how common is a complete lack of access to imaging? And what are the correct public policy tools to address it? 

  • In the new study, researchers assessed imaging availability in U.S. counties by determining whether imaging equipment, local radiologists, or both were available. 

In their analysis of 3.1k U.S. counties covering 340.1M residents, researchers found…

  • Only 1.9% of Americans (6.4M people) lived in true imaging deserts, where there was neither installed imaging equipment nor a local practicing radiologist.
  • 7.6% of Americans (25.9M people) lived in counties with an installed scanner but no local radiologist.
  • 0.1% lived in a county with a local radiologist but no equipment.
  • 90% (307.4M) were considered “fully served” by imaging, with local image acquisition available and some kind of remote interpretation possible.

The statistics point to radiology’s advantage over other medical specialties that require doctors to be physically present to deliver care.

  • Thanks to teleradiology, images can be acquired locally with installed equipment and then transmitted to central hubs for interpretation. 

But even if less than 2% of the population lacks access, 6.4M Americans is a lot of people. How does living in an imaging desert affect their access to radiology? 

  • Researchers found that imaging use rates were 6% lower in imaging deserts compared to fully served regions, while Medicare payments per beneficiary were 8.9% lower. 

The Takeaway

The new findings on regional access to imaging show that while most Americans have good access to radiology services, more work is needed to improve care for those who don’t. This is particularly true for services like interventional radiology that require radiologists to be present. 

Is It Time for Mammography AI?

Is AI ready for widespread use in mammography screening? That question was the focus of a point-counterpoint debate in AJR that discussed the pros and cons of broad-based clinical AI deployment for one of radiology’s most high-profile exams. 

Mammography screening is perhaps the clinical use case with the most potential to help radiologists drowning under a rising tide of imaging exams.

  • Several large-scale research studies have been published recently – mostly in Europe – showing that, for most normal mammograms, AI could reduce the need for a second reader, as is common in European screening programs.

Indeed, mammography AI developer Lunit last week announced a contract with a Swedish health system that would do just that, having AI act as an autonomous second reader. 

  • While the U.S. doesn’t typically use second readers for breast screening, AI could still play an important role in assisting radiologists in interpreting mammograms, predicting patient risk, and acting as a sort of clinical spell-check to reduce misses.

So does that mean mammography AI is ready for prime time? Taking the skeptical view were Duke University breast radiologists Eun Langman, MD, and Vilert Loving, MD, who believe caution is warranted, for the following reasons…

  • Most of AI’s reported diagnostic performance gains have been with 2D digital mammography, and may not apply to DBT mammography, which has become the standard in the U.S.
  • While autonomous AI interpretation of mammograms has been touted, there are practical barriers to its widespread application, such as the legal implications of AI misses.
  • There is no evidence showing AI reduces breast cancer mortality, and there are many other interventions that could do so at a lower cost.

Taking the other side of the argument was MGH breast radiologist Manisha Bahl, MD, who noted that…

  • Evidence supporting mammography AI’s effectiveness has come not only from randomized controlled trials like MASAI, but also from studies of routine population-based screening like the PRAIM study in Germany. 
  • Studies of mammography AI in the U.S. – where DBT is routinely used – have shown cancer detection gains comparable to those in Europe.
  • In addition to diagnostic support, AI can speed radiologist workflow, such as through autonomous AI reporting of some mammograms.

The Takeaway

In the debate over mammography AI deployment, both sides present persuasive arguments. But as is the case with AI applications outside healthcare, the technological imperative to leverage this powerful new technology is likely to swamp any attempts to put up guardrails restricting its use.

Get every issue of The Imaging Wire, delivered right to your inbox.