When Chest CT Needs a Functional Layer

Regional lung function is emerging as an important factor in thoracic imaging. While chest CT is central to evaluating lung disease, anatomy (structure) alone does not always explain the full clinical challenge. Fortunately, a new generation of CT-based software tools brings regional lung function into the workflow radiologists use every day – chest CT.

Patients with dyspnea, COPD, emphysema, interstitial lung disease, or pulmonary vascular questions can often have symptoms that are difficult to reconcile with structural findings alone.

Radiologists and clinicians assemble the broader clinical picture from multiple sources: CT findings, pulmonary function tests, and nuclear medicine ventilation/perfusion (V/Q) exams. 

  • Each offers useful information, but each has limits. Pulmonary function tests provide global measures rather than regional detail, while V/Q imaging depends on radiotracer availability, department hours, and nuclear medicine resources.

One example of an emerging technology that provides radiologists with deeper, functional pulmonary detail is CT:VQ from 4DMedical. 

  • CT:VQ, operating in a Software as a Service (SaaS) mode, uses paired inspiratory and expiratory non-contrast chest CT scans to generate regional ventilation and perfusion maps – along with quantitative outputs designed for radiology workflow.

This approach brings functional lung information closer to the CT reading room without requiring injected contrast or radiotracers for the CT:VQ analysis. 

  • It also builds on a modality that is widely available and often operational around the clock.

Adding regional ventilation and perfusion information to CT could help address common thoracic imaging questions…

  • Which regions are ventilating well, and which are not?
  • Is perfusion preserved in areas that look abnormal on CT?
  • Do symptoms align with regional functional impairment?
  • Which lung regions may be most important to preserve before intervention?

The non-contrast approach has compelling clinical advantages… 

  • Contrast can trigger renal screening, prior reaction history, IV access challenges, workflow delays, and patient anxiety. 
  • Avoiding contrast can simplify the pathway for many patients.

CT-based functional imaging is not a replacement for legacy lung function assessments. But it brings quantitative tools that can make routine studies more clinically actionable.

The Takeaway

Technology brings radiologists new opportunities. Chest CT can reveal far more than what the lungs look like. With tools such as CT:VQ, CT can show regional patterns of lung ventilation and perfusion – adding functional context to a radiologist’s toolkit.

More information about CT:VQ and non-contrast functional lung imaging is available at ctvq.com.

What Now for the USPSTF?

After not meeting for over a year and undergoing major turnover, HHS Secretary Robert F. Kennedy, Jr. last week announced new members of the U.S. Preventive Services Task Force – including the USPSTF’s first-ever radiologist. 

USPSTF was created in 1984 as a panel of experts tasked with producing evidence-based advice on preventive medical care, like cancer screening guidelines. 

  • But it’s that last responsibility that’s drawn the USPSTF into controversy. The group in 2009 changed its blanket recommendation regarding screening mammography for women aged 40 to 50, instead recommending women consult with their doctors. This sparked a backlash that persisted until 2023, when it said it would lower the age back down to 40. 

Indeed, the USPSTF has often been accused of being too conservative in recommending new technologies that have life-saving potential. 

  • For example, its implementation of the new mammography screening guidelines neglected to recommend supplemental dense breast screening, despite the demonstrated connection between dense breasts and cancer risk.

Enter RFK, Jr., who as HHS secretary has appointment authority over the panel’s 16 members (who, it should be noted, serve as volunteers rather than as federal employees).

  • He’s held the USPSTF with the same suspicion he reserves for the rest of the U.S. medical establishment, and on his watch the group has gone a year and a half without a meeting. He also removed both of the panel’s vice chairs in May. 

RFK, Jr. hadn’t revealed much about his intentions for the panel, but that ended on September 17, when HHS announced a new slate of appointments. 

  • He tapped eight new members, including a number of medical specialists, addressing a frequent criticism that the USPSTF was too heavily weighted toward primary care and lacked specialty experience. 

And in what is a first, he named a radiologist to the USPSTF: Dennis Wulfeck, MD, of MBB Radiology, a Radiology Partners-affiliated practice in Jacksonville, Florida. 

  • Wulfeck earned his MD at Wright State University, performed his residency at the University of Louisville, and completed a fellowship in nuclear medicine at the University of Cincinnati. Wulfeck has published research in nuclear medicine and has been involved in radiology practice issues. 

What now for the USPSTF? While the new appointments seem to represent physicians from U.S. medicine’s mainstream, their work will be closely scrutinized for signs of politicization, particularly around RFK, Jr.’s pet issue of childhood vaccines. The USPSTF hasn’t said when its next meeting will take place. 

The Takeaway

Radiology has long had a complicated relationship with the USPSTF, mostly due to its conservative stances on cancer screening and the adoption of new imaging technologies. Will that change with a radiologist now serving on the panel? We shall see. 

Cancer Survival Rates Rise as AI’s Impact Looms

More people are surviving cancer in the U.S. than ever before, even as the number of new U.S. cancer cases is expected to increase 19% by 2050. The AACR’s 2026 Cancer Progress Report showed rising cancer survival rates – especially for breast and lung cancer – and new technologies like AI could drive survival even higher.

The AACR report revealed big improvements in treatment and clinical outcomes…

  • The overall five-year survival rate for distant-stage cancer is more than double what it was three decades ago (17% to 36%). 
  • Since July 2025, the FDA approved 11 new anticancer therapies and additional uses for five existing interventions.

While that progress is coming fast, it has stalled in some areas… 

  • The pancreatic cancer survival rate remains low at 14%, compared with 92% for breast cancer and 98% for prostate cancer.
  • Disparities persist: Black men and American Indian/Alaska Native women had the highest cancer incidence rates from 2019 to 2023.
  • Across the same period, lung cancer rates were 37% higher in rural versus metropolitan areas.

Breast and lung cancer rank second and third for new diagnoses in the U.S., but advances in imaging-based screening for these cancers are accelerating… 

  • The U.S. breast cancer mortality rate declined by 44% from 1989 to 2024.
  • Breast cancer death rates have been decreasing by 1.2% per year.
  • Efforts to promote earlier detection are occurring, such as the USPSTF’s lowering of the recommended mammography screening age to 40.
  • Declines in lung cancer mortality accounted for the largest share of cancer deaths averted from 1975 to 2020, partly because of tobacco-control programs. 

But screening continues to be an essential tool to drive cancer mortality down even more, and AI could become a handy helper.

  • The MASAI trial found that AI-supported screening was associated with a 12% lower rate of interval cancers.
  • AI-assisted mammography detected early-stage breast cancer with greater sensitivity than standard screening without sacrificing specificity.
  • The report cited two recently cleared AI tools that can help with early detection: RevealDx’s RevealAI-Lung, which reportedly reduced false positives by 18%, and Median Technologies’ eyonis LCS, which showed 93% sensitivity in tests.

The tools could also help radiologists cope with the ongoing workforce shortage by stepping in as second readers or prioritizing high-risk cases. 

  • AI assistance could decrease reading workload by 44%, per the AACR report.

The Takeaway 

The AACR’s report shows encouraging progress in the war on cancer. In the future, AI advances could help radiologists continue to improve screening for lung and breast cancer patients, with some promising early evidence.

Expanding CT Lung Screening at WCLC 2026

Low-dose CT lung cancer screening appears set to be the next major population-based cancer screening exam. But much work remains to make LDCT screening available to as many eligible people as possible while optimizing scanning protocols.

That’s according to sessions at IASLC’s World Conference on Lung Cancer (WCLC 2026), which just wrapped up in Seoul, South Korea. 

  • WCLC 2026 sessions ranged from expanding scanning to people at high risk but without smoking histories to using AI to not only detect and characterize lung nodules but to predict future cancer risk.

Some of the key findings from WCLC 2026 included…

  • Australia started its national LDCT screening program in 2025, and researchers expect a national-level stage shift to earlier diagnosis. At a 50% participation rate, stage I diagnoses should grow from 32% currently to 42% for women and 43% for men. 
  • The Ready to Screen (R2S) trial in Australia found that of 1.7k eligible screening candidates surveyed, 85% “definitely” intended to get screened and 26% said they had already received an LDCT scan. 
  • Taiwan’s national screening program showed that – at least in East Asia – people with a family history of lung cancer should be screened. Of 2.8k cancers detected, there was a 74% higher detection rate in those with family histories versus smoking histories (18 vs. 10 cancers per 1k screened), with more early-stage cancers detected (92% vs. 83%).
  • An LDCT screening program in China screened 6.7k people – including those with risk factors besides smoking – finding a 56% lung cancer mortality reduction.  
  • French clinicians successfully added smoking cessation therapy to their LDCT program, with 88% screening attendance and participants 44% less likely to smoke.
  • MIT’s Sybil AI algorithm was more accurate than Lung-RADS in predicting one-year cancer risk from suspicious nodules, with higher AUC when applied to two large lung screening trials (NLST and P-IELCAP). 
  • Researchers found that applying Sybil to coronary artery calcium scans could also predict lung cancer risk for both smokers and non-smokers over a 15-year follow-up period.
  • Researchers used Softek Illuminate’s Illuminate AI software for identifying incidental pulmonary nodules as a complement to an LDCT screening program, finding that the algorithm discovered more lung cancer cases than conventional screening. 

The Takeaway

This week’s WCLC 2026 sessions point out the rapid progress being made around the world in expanding access to LDCT lung cancer screening – as well as the role that AI-based software tools can play in making screening more effective and more widely accessible. 

Top 10 AI Vendors by FDA Approvals

The FDA updated its list of regulatory authorizations for AI-enabled medical devices, covering approvals granted through the end of June 2026. The new numbers show radiology maintaining its strong lead over other medical specialties. 

The FDA issues quarterly updates on marketing authorizations for AI-enabled products, a category that includes dedicated software applications as well as AI-enhanced hardware, like scanners with onboard AI functionality. 

  • The list is closely watched by healthcare industry observers, and radiology has typically secured more than three-quarters of the authorizations – not surprising given the specialty’s image-intensive nature. 

The most recent list tracks FDA actions through the end of June 2026, indicating that the FDA has…

  • Authorized 1,614 AI-enabled medical devices since it started keeping track, up 5.9% from Q1 2026. 
  • Authorized 1,230 radiology devices, or 76% of all AI-enabled medical authorizations. 
  • In the second quarter of 2026, the FDA authorized 89 AI-enabled medical devices, slightly fewer than the 92 devices it authorized in the first quarter of 2026. 
  • For the quarter, 66 authorizations (74%) were for radiology devices, similar to the Q1 ratio (75%).
  • GE HealthCare maintained its AI authorizations lead with 134, thanks in part to approvals secured by companies it has acquired over the years. 
  • Next are Siemens Healthineers at 101, then Philips at 62, Canon at 51, United Imaging at 45, Aidoc at 34, and DeepHealth at 32, with all numbers including acquisitions. 
  • Rounding out the top 10 are Samsung (21), RapidAI (20), and Hyperfine (13).

The Takeaway

The new numbers track pretty closely with data on AI-enabled regulatory authorizations the FDA released for the first quarter. It will be interesting to see whether the agency’s pace changes as it comes to a final decision on regulating generative AI algorithms used for direct clinical care – a task for which it is currently soliciting feedback. 

Harrison’s Teleradiology Play

AI developer Harrison.ai is expanding its business model by supporting a teleradiology venture called Frontier Radiology that’s scaling up and hiring radiologists. But the move drew unwanted attention from a critical article in the Australian news media this week.

Harrison is best known for its suite of AI algorithms for radiology applications, as well as its Harrison.Rad 1.5 foundation model that can draft reports for radiologist review.

  • Harrison is based in Australia, but has recently made the U.S. market a major focus, with co-founder and managing director Dimitry Tran relocating to California to spearhead the initiative.

But it was Harrison’s newfound U.S. focus that apparently drew the attention of ABC News, an Australian news outlet that on September 7 published a critical article that questioned the company’s moves, in particular its involvement with Frontier Radiology.

  • One bone of contention in the story was whether Harrison’s U.S. emphasis was appropriate given the Australian government’s 2025 investment of US$23M in the company. The story also claimed Harrison was planning layoffs of Australian staff and that its integration of AI with Frontier’s clinical services could be a conflict of interest.

But in an interview with The Imaging Wire, Dimitry Tran clarified Harrison’s strategic direction and its involvement with Frontier Radiology.  

  • Tran noted that Frontier is owned and operated by a radiologist – Joshua Ewell, DO – in accordance with U.S. rules requiring physician ownership of entities providing clinical services. 

Ewell’s LinkedIn profile says Frontier will be an “AI-native radiology group” built entirely around AI foundation models.

  • Harrison is providing Frontier with non-clinical services, including its suite of AI algorithms, which are already helping Frontier teleradiologists achieve industry-leading report turnaround times. But Frontier radiologists are free to use any AI solutions they wish – including those of Harrison’s competitors. 

Tran noted that close cooperation between AI developers and imaging services providers is hardly unusual anymore in radiology. 

  • Indeed, two of the specialty’s largest U.S. providers – Radiology Partners and RadNet – have formed their own AI divisions to provide algorithms to both their own radiologists and outside customers. 

The ABC News article conflated a number of recent developments into a narrative that doesn’t reflect reality, Tran believes. 

  • For example, the layoffs that occurred earlier this year at Harrison were connected to the company’s transition from an aggressive R&D phase into a commercialization push and weren’t related to Harrison’s U.S. entry.

And the Australian government’s funding was part of an investment that gave it a single-digit equity stake in the company – a stake it retains to this day and that will prove increasingly profitable with Harrison’s growing success.

  • Even as it supports Frontier, Harrison plans to continue its focus on AI algorithm development and commercialization, especially of the Harrison.Rad foundation model – while keeping the “vast majority” of its employees in Australia. 

The Takeaway

Putting aside the ABC article’s negative spin, Harrison’s move into teleradiology offers an intriguing twist on the growing integration between AI and imaging services providers. Given ongoing workforce shortages and rising imaging volume, it’s perhaps the best way to move the chains toward finding relief for beleaguered radiologists. 

VA Radiologist Exodus ‘Tip of Iceberg’

A “mass exodus” of radiologists from the VA’s medical center in Washington, DC, represents just the tip of the iceberg for the health system’s radiology personnel woes. Other VA centers are reported to have seen similar departures, and the VA’s teleradiology program appears to be buckling under the strain. 

News about radiologist staffing problems in the VA came to light in July with the publication of news articles claiming that the Trump administration’s 2025 ban on remote work for federal employees had prompted most radiologists at the VA Washington DC Medical Center to quit.

  • While the ban was later rescinded for radiologists, the edict reportedly “spooked” many radiologists who were already chafing under VA salaries that were far lower than what they could find in the private sector.  

An investigation by the VA’s Office of Inspector General confirmed the Washington, DC, medical center’s problems, documenting the departure of four of the facility’s five full-time radiologists as well as its chief of radiology.

  • But the question remained – how widespread are the VA’s radiologist staffing woes, and have the same problems occurred at other VA medical centers?

Indications are that it’s a growing problem. A VA employee who contacted The Imaging Wire reported that VA radiology departments around the U.S. “got decimated,” with some losing 50% of their radiologist staff.

  • This includes VA medical centers in Houston, Dallas, and San Antonio, and a number in Florida. 

Interestingly, the source claims that the return-to-office edict has only been a “minor” contributor to the exodus, instead attributing the departures to a vicious cycle of lower salaries and higher workload. 

  • The VA’s salary cap of $400k simply isn’t competitive with private-sector radiology, where a recent compensation survey pegged average U.S. radiologist compensation at $610k – a 53% difference. 

The shortage of in-person radiologists is prompting the VA to lean more heavily on its National Teleradiology Program, an operation headquartered in Menlo Park, California, that employs dozens of radiologists to interpret imaging studies overnight and on weekends.

  • But NTP is facing a personnel exodus of its own, especially after NTP officials required daytime radiologists to pick up the slack by also working nights and every other weekend. The source estimated that, at its peak, NTP had about 120 radiologists. That number now stands at 62.

What impact are the departures having on VA patient care? The VA mandates a one-hour turnaround time (TAT) for STAT imaging exams. 

  • But the source claims that TAT has ballooned to as high as 10 hours. “Imagine not getting critical diagnoses for ER patients until 10-12 hours later!” the source said.

The Takeaway

The new revelations suggest that the problems reported at the VA Washington DC Medical Center are actually endemic throughout the VA system. And given the growing gap between VA and private radiologist salaries, they aren’t likely to recede anytime soon, regardless of the agency’s work-from-home policies.

PET Tracer for Cardiac Amyloidosis Shows Promise

New results were presented this weekend on a PET radiopharmaceutical being developed by Bayer for imaging cardiac amyloidosis. The tracer turned in promising results in a paper presented at ESC 2026 and published simultaneously in JAMA.

Cardiac amyloidosis occurs when abnormal proteins called amyloid fibrils build up in heart tissue, eventually leading to heart failure and death. It was once thought to be untreatable, but new pharmaceutical therapies have become available that slow disease progression and improve patient outcomes. 

  • But first you have to make a diagnosis, and that’s been the hard part. Multiple imaging modalities are often required, and patients with cardiac amyloidosis often experience diagnostic delays of one to two years or more.

Enter Bayer, which earlier this year acquired a pair of radiopharmaceuticals from Attralus, one for PET imaging and the other for SPECT. The PET agent is iodine-124 evuzamitide, a radiolabeled synthetic peptide that binds to the amyloid fibrils that characterize cardiac amyloidosis. 

  • The acquisition was a bit of a departure for Bayer, which until the purchase had focused its imaging business mostly on contrast agents for X-ray, CT, and MRI. 

But the results presented over the weekend from the Phase III REVEAL trial indicate Bayer may have placed a good bet. 

  • Researchers enrolled 170 patients from 18 U.S. centers who got PET/CT scans with iodine-124 evuzamitide. Three physicians with experience in cardiac PET/CT reviewed the results.

The REVEAL investigators discovered…

  • Iodine-124 evuzamitide had 94% sensitivity for cardiac amyloidosis, with 86% specificity. 
  • Positive predictive value was 85%, and negative predictive value was 94%.  
  • The radiotracer showed high diagnostic accuracy for both types of cardiac amyloidosis, light chain (AL) and transthyretin (ATTR) amyloidosis.
  • The radiotracer was well tolerated by patients. 

The findings indicate that iodine-124 evuzamitide has potential “as a reliable first-line test to exclude cardiac amyloidosis,” meaning it could rule out the need for invasive biopsy. 

  • What next for the tracer? Bayer said it would be discussing the REVEAL data as well as regulatory submissions with the FDA and other health authorities.

The Takeaway

New results from REVEAL indicate that Bayer’s iodine-124 evuzamitide PET radiotracer has the potential to fundamentally change the diagnosis of cardiac amyloidosis, historically one of the more challenging heart conditions to detect and manage. 

Radiology Salary Growth Beats Other Specialties

Radiologists enjoyed faster salary growth than physicians overall in the latest salary survey from Doximity. Radiologists also moved up several positions on the list of highest-paid doctors. 

Doximity operates a widely used digital platform that counts around 85% of U.S. physicians as members. 

  • The company’s annual salary survey is a closely watched barometer of physician compensation, as well as other trends like compensation by metro area and physician specialty. 

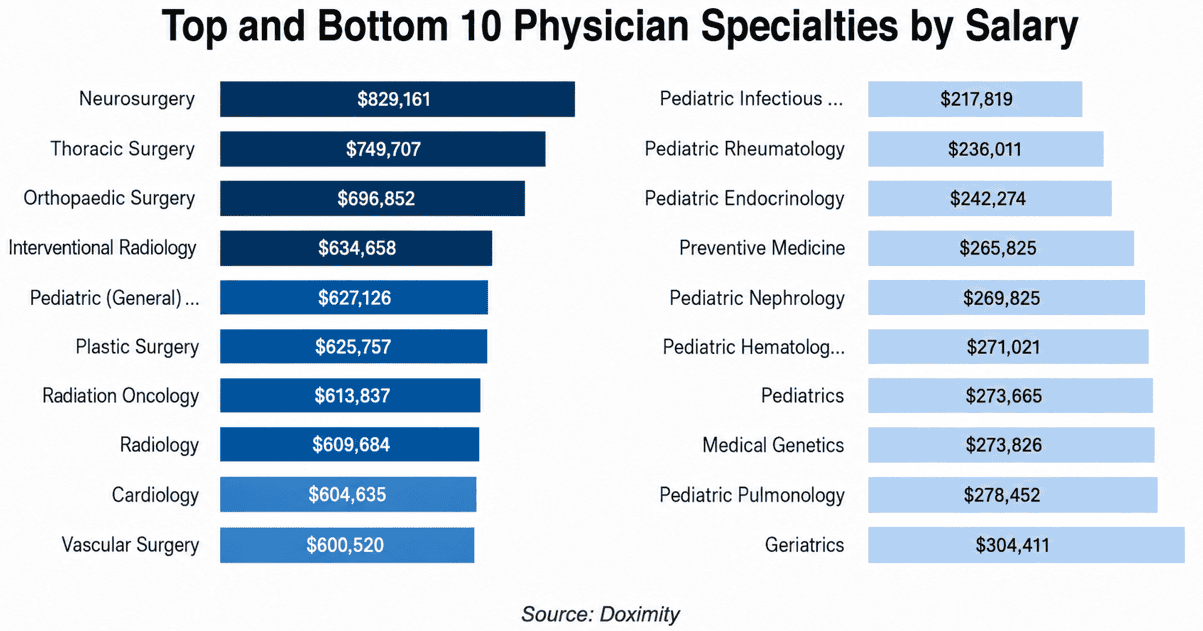
The 2026 survey found that radiologists had an average annual salary of $610k, up 6.6% compared to $572k in the last survey. Radiology’s growth exceeded the 2% average growth rate for all physician specialties. 

  • Radiology moved up three positions to occupy the #8 slot among highest-paid specialties, compared to #11 in last year’s survey. 

Despite radiology’s progress, salary growth in the specialty actually slowed a bit compared to Doximity’s 2025 survey, when it rose 7.5%. 

  • Back then, radiology had the fourth-fastest salary growth among medical specialists. 

Count yourself lucky if you’re an interventional radiologist. The field saw the largest increase in annual compensation among all physician specialties – 10.8%, bringing average compensation to $635k.

Besides just compensation, the 2026 survey also queried physicians about other employment-related topics, finding…

  • 85% reported that the physician shortage had affected their clinical practice.
  • 76% said the shortage and other pressures had compromised the quality of care they deliver.
  • The gender salary gap remained at 26% for the second straight year as men made an average of $122k more than women.
  • At 10%, radiology actually had one of the smallest gender pay gaps.

The survey also drilled down into physician attitudes toward artificial intelligence, which is being proffered as a potential solution to the workforce shortage, finding that…

  • 66% reported using AI on a daily or weekly basis.
  • 23% expected AI to boost their compensation within the next year.
  • 67% thought that doctors who stay current with AI tools will have an earnings advantage over physicians who don’t.

The Takeaway

The new Doximity physician survey showed that despite workload challenges, radiology remains one of the best-compensated physician specialties. It also highlights physicians’ changing attitudes toward AI, as what was once seen as a competitive force is now viewed as a complementary and even beneficial technology for doctors.

Could MRI Reduce Prostate Biopsies?

Could MRI one day reduce the need to biopsy some patients with suspected prostate cancer before they get treatment? U.K. researchers raise that intriguing prospect in a new study in European Journal of Radiology. 

Biopsy is an integral part of the workup protocol for men suspected of having prostate cancer, typically due to their elevated PSA levels.

  • But prostate biopsy is an invasive procedure, and can cause both complications and anxiety in patients, as well as contribute to higher healthcare costs.

MRI has proven effective in selecting which patients should be sent for biopsy and which ones can be followed with active surveillance – thus avoiding biopsy’s negative consequences.

  • But what if you could eliminate biopsy altogether in some men by making the diagnosis directly with MRI, and sending patients straight to treatment? 

That’s what researchers from University College Hospital in London tried in the new EJR paper by studying 880 consecutive patients who presented to their prostate clinic and got multiparametric MRI scans. Of these, 251 were considered suspicious for disease based on their scans.

  • Radiologists interpreted the images, focusing specifically on cases where they were 99% certain that the suspected lesion was cancerous, but also grading cases at 90% and <90% certainty. Indeterminate cases could be forwarded to biopsy for further investigation.

Researchers discovered…

  • 79 patients (9% of the total) were in the “99% certain” category, with 69 going to biopsy – and 100% had clinically significant tumors.
  • 45 patients (5% of the total) were in the “90% certain” category, with 41 undergoing biopsy and 98% having clinically significant tumors.
  • The combined groups represented 14% of the patients presenting to the clinic and 49% of the suspicious cases, and only one individual did not have a clinically significant tumor.

Applying the findings to real-world clinical practice, patients in the “99% certain” or “90% certain” categories could be sent straight to prostatectomy, without the need for biopsy or PSMA-PET scans.

  • Such a straight-to-treatment protocol would be analogous to the treatment of kidney and testicular cancer, where patients are treated without biopsy on the basis of imaging scans that are definitive for cancer. 

The Takeaway

Previous studies have found that MRI can reduce biopsies in men with low suspicion of serious disease, instead directing them to active surveillance. The new research shows MRI also works at the other end of the spectrum, sparing men with clinically significant cancer the ordeal of undergoing biopsy before they can start their treatment.

Get every issue of The Imaging Wire, delivered right to your inbox.