Top 10 AI Vendors by FDA Approvals

The FDA updated its list of regulatory authorizations for AI-enabled medical devices, covering approvals granted through the end of June 2026. The new numbers show radiology maintaining its strong lead over other medical specialties. 

The FDA issues quarterly updates on marketing authorizations for AI-enabled products, a category that includes dedicated software applications as well as AI-enhanced hardware, like scanners with onboard AI functionality. 

  • The list is closely watched by healthcare industry observers, and radiology has typically secured more than three-quarters of the authorizations – not surprising given the specialty’s image-intensive nature. 

The most recent list tracks FDA actions through the end of June 2026, indicating that the FDA has…

  • Authorized 1,614 AI-enabled medical devices since it started keeping track, up 5.9% from Q1 2026. 
  • Authorized 1,230 radiology devices, or 76% of all AI-enabled medical authorizations. 
  • In the second quarter of 2026, the FDA authorized 89 AI-enabled medical devices, slightly fewer than the 92 devices it authorized in the first quarter of 2026. 
  • For the quarter, 66 authorizations (74%) were for radiology devices, similar to the Q1 ratio (75%).
  • GE HealthCare maintained its AI authorizations lead with 134, thanks in part to approvals secured by companies it has acquired over the years. 
  • Next are Siemens Healthineers at 101, then Philips at 62, Canon at 51, United Imaging at 45, Aidoc at 34, and DeepHealth at 32, with all numbers including acquisitions. 
  • Rounding out the top 10 are Samsung (21), RapidAI (20), and Hyperfine (13).

The Takeaway

The new numbers track pretty closely with data on AI-enabled regulatory authorizations the FDA released for the first quarter. It will be interesting to see whether the agency’s pace changes as it comes to a final decision on regulating generative AI algorithms used for direct clinical care – a task for which it is currently soliciting feedback. 

Harrison’s Teleradiology Play

AI developer Harrison.ai is expanding its business model by supporting a teleradiology venture called Frontier Radiology that’s scaling up and hiring radiologists. But the move drew unwanted attention from a critical article in the Australian news media this week.

Harrison is best known for its suite of AI algorithms for radiology applications, as well as its Harrison.Rad 1.5 foundation model that can draft reports for radiologist review.

  • Harrison is based in Australia, but has recently made the U.S. market a major focus, with co-founder and managing director Dimitry Tran relocating to California to spearhead the initiative.

But it was Harrison’s newfound U.S. focus that apparently drew the attention of ABC News, an Australian news outlet that on September 7 published a critical article that questioned the company’s moves, in particular its involvement with Frontier Radiology.

  • One bone of contention in the story was whether Harrison’s U.S. emphasis was appropriate given the Australian government’s 2025 investment of US$23M in the company. The story also claimed Harrison was planning layoffs of Australian staff and that its integration of AI with Frontier’s clinical services could be a conflict of interest.

But in an interview with The Imaging Wire, Dimitry Tran clarified Harrison’s strategic direction and its involvement with Frontier Radiology.  

  • Tran noted that Frontier is owned and operated by a radiologist – Joshua Ewell, DO – in accordance with U.S. rules requiring physician ownership of entities providing clinical services. 

Ewell’s LinkedIn profile says Frontier will be an “AI-native radiology group” built entirely around AI foundation models.

  • Harrison is providing Frontier with non-clinical services, including its suite of AI algorithms, which are already helping Frontier teleradiologists achieve industry-leading report turnaround times. But Frontier radiologists are free to use any AI solutions they wish – including those of Harrison’s competitors. 

Tran noted that close cooperation between AI developers and imaging services providers is hardly unusual anymore in radiology. 

  • Indeed, two of the specialty’s largest U.S. providers – Radiology Partners and RadNet – have formed their own AI divisions to provide algorithms to both their own radiologists and outside customers. 

The ABC News article conflated a number of recent developments into a narrative that doesn’t reflect reality, Tran believes. 

  • For example, the layoffs that occurred earlier this year at Harrison were connected to the company’s transition from an aggressive R&D phase into a commercialization push and weren’t related to Harrison’s U.S. entry.

And the Australian government’s funding was part of an investment that gave it a single-digit equity stake in the company – a stake it retains to this day and that will prove increasingly profitable with Harrison’s growing success.

  • Even as it supports Frontier, Harrison plans to continue its focus on AI algorithm development and commercialization, especially of the Harrison.Rad foundation model – while keeping the “vast majority” of its employees in Australia. 

The Takeaway

Putting aside the ABC article’s negative spin, Harrison’s move into teleradiology offers an intriguing twist on the growing integration between AI and imaging services providers. Given ongoing workforce shortages and rising imaging volume, it’s perhaps the best way to move the chains toward finding relief for beleaguered radiologists. 

VA Radiologist Exodus ‘Tip of Iceberg’

A “mass exodus” of radiologists from the VA’s medical center in Washington, DC, represents just the tip of the iceberg for the health system’s radiology personnel woes. Other VA centers are reported to have seen similar departures, and the VA’s teleradiology program appears to be buckling under the strain. 

News about radiologist staffing problems in the VA came to light in July with the publication of news articles claiming that the Trump administration’s 2025 ban on remote work for federal employees had prompted most radiologists at the VA Washington DC Medical Center to quit.

  • While the ban was later rescinded for radiologists, the edict reportedly “spooked” many radiologists who were already chafing under VA salaries that were far lower than what they could find in the private sector.  

An investigation by the VA’s Office of Inspector General confirmed the Washington, DC, medical center’s problems, documenting the departure of four of the facility’s five full-time radiologists as well as its chief of radiology.

  • But the question remained – how widespread are the VA’s radiologist staffing woes, and have the same problems occurred at other VA medical centers?

Indications are that it’s a growing problem. A VA employee who contacted The Imaging Wire reported that VA radiology departments around the U.S. “got decimated,” with some losing 50% of their radiologist staff.

  • This includes VA medical centers in Houston, Dallas, and San Antonio, and a number in Florida. 

Interestingly, the source claims that the return-to-office edict has only been a “minor” contributor to the exodus, instead attributing the departures to a vicious cycle of lower salaries and higher workload. 

  • The VA’s salary cap of $400k simply isn’t competitive with private-sector radiology, where a recent compensation survey pegged average U.S. radiologist compensation at $610k – a 53% difference. 

The shortage of in-person radiologists is prompting the VA to lean more heavily on its National Teleradiology Program, an operation headquartered in Menlo Park, California, that employs dozens of radiologists to interpret imaging studies overnight and on weekends.

  • But NTP is facing a personnel exodus of its own, especially after NTP officials required daytime radiologists to pick up the slack by also working nights and every other weekend. The source estimated that, at its peak, NTP had about 120 radiologists. That number now stands at 62.

What impact are the departures having on VA patient care? The VA mandates a one-hour turnaround time (TAT) for STAT imaging exams. 

  • But the source claims that TAT has ballooned to as high as 10 hours. “Imagine not getting critical diagnoses for ER patients until 10-12 hours later!” the source said.

The Takeaway

The new revelations suggest that the problems reported at the VA Washington DC Medical Center are actually endemic throughout the VA system. And given the growing gap between VA and private radiologist salaries, they aren’t likely to recede anytime soon, regardless of the agency’s work-from-home policies.

PET Tracer for Cardiac Amyloidosis Shows Promise

New results were presented this weekend on a PET radiopharmaceutical being developed by Bayer for imaging cardiac amyloidosis. The tracer turned in promising results in a paper presented at ESC 2026 and published simultaneously in JAMA.

Cardiac amyloidosis occurs when abnormal proteins called amyloid fibrils build up in heart tissue, eventually leading to heart failure and death. It was once thought to be untreatable, but new pharmaceutical therapies have become available that slow disease progression and improve patient outcomes. 

  • But first you have to make a diagnosis, and that’s been the hard part. Multiple imaging modalities are often required, and patients with cardiac amyloidosis often experience diagnostic delays of one to two years or more.

Enter Bayer, which earlier this year acquired a pair of radiopharmaceuticals from Attralus, one for PET imaging and the other for SPECT. The PET agent is iodine-124 evuzamitide, a radiolabeled synthetic peptide that binds to the amyloid fibrils that characterize cardiac amyloidosis. 

  • The acquisition was a bit of a departure for Bayer, which until the purchase had focused its imaging business mostly on contrast agents for X-ray, CT, and MRI. 

But the results presented over the weekend from the Phase III REVEAL trial indicate Bayer may have placed a good bet. 

  • Researchers enrolled 170 patients from 18 U.S. centers who got PET/CT scans with iodine-124 evuzamitide. Three physicians with experience in cardiac PET/CT reviewed the results.

The REVEAL investigators discovered…

  • Iodine-124 evuzamitide had 94% sensitivity for cardiac amyloidosis, with 86% specificity. 
  • Positive predictive value was 85%, and negative predictive value was 94%.  
  • The radiotracer showed high diagnostic accuracy for both types of cardiac amyloidosis, light chain (AL) and transthyretin (ATTR) amyloidosis.
  • The radiotracer was well tolerated by patients. 

The findings indicate that iodine-124 evuzamitide has potential “as a reliable first-line test to exclude cardiac amyloidosis,” meaning it could rule out the need for invasive biopsy. 

  • What next for the tracer? Bayer said it would be discussing the REVEAL data as well as regulatory submissions with the FDA and other health authorities.

The Takeaway

New results from REVEAL indicate that Bayer’s iodine-124 evuzamitide PET radiotracer has the potential to fundamentally change the diagnosis of cardiac amyloidosis, historically one of the more challenging heart conditions to detect and manage. 

Radiology Salary Growth Beats Other Specialties

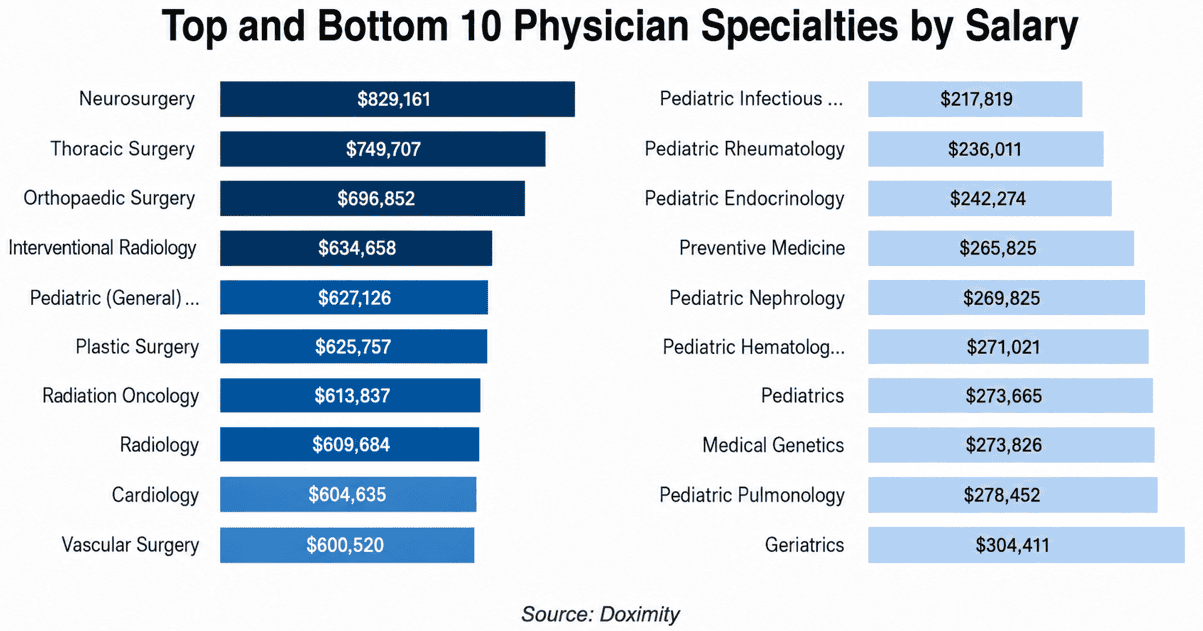
Radiologists enjoyed faster salary growth than physicians overall in the latest salary survey from Doximity. Radiologists also moved up several positions on the list of highest-paid doctors. 

Doximity operates a widely used digital platform that counts around 85% of U.S. physicians as members. 

  • The company’s annual salary survey is a closely watched barometer of physician compensation, as well as other trends like compensation by metro area and physician specialty. 

The 2026 survey found that radiologists had an average annual salary of $610k, up 6.6% compared to $572k in the last survey. Radiology’s growth exceeded the 2% average growth rate for all physician specialties. 

  • Radiology moved up three positions to occupy the #8 slot among highest-paid specialties, compared to #11 in last year’s survey. 

Despite radiology’s progress, salary growth in the specialty actually slowed a bit compared to Doximity’s 2025 survey, when it rose 7.5%. 

  • Back then, radiology had the fourth-fastest salary growth among medical specialists. 

Count yourself lucky if you’re an interventional radiologist. The field saw the largest increase in annual compensation among all physician specialties – 10.8%, bringing average compensation to $635k.

Besides just compensation, the 2026 survey also queried physicians about other employment-related topics, finding…

  • 85% reported that the physician shortage had affected their clinical practice.
  • 76% said the shortage and other pressures had compromised the quality of care they deliver.
  • The gender salary gap remained at 26% for the second straight year as men made an average of $122k more than women.
  • At 10%, radiology actually had one of the smallest gender pay gaps.

The survey also drilled down into physician attitudes toward artificial intelligence, which is being proffered as a potential solution to the workforce shortage, finding that…

  • 66% reported using AI on a daily or weekly basis.
  • 23% expected AI to boost their compensation within the next year.
  • 67% thought that doctors who stay current with AI tools will have an earnings advantage over physicians who don’t.

The Takeaway

The new Doximity physician survey showed that despite workload challenges, radiology remains one of the best-compensated physician specialties. It also highlights physicians’ changing attitudes toward AI, as what was once seen as a competitive force is now viewed as a complementary and even beneficial technology for doctors.

Could MRI Reduce Prostate Biopsies?

Could MRI one day reduce the need to biopsy some patients with suspected prostate cancer before they get treatment? U.K. researchers raise that intriguing prospect in a new study in European Journal of Radiology. 

Biopsy is an integral part of the workup protocol for men suspected of having prostate cancer, typically due to their elevated PSA levels.

  • But prostate biopsy is an invasive procedure, and can cause both complications and anxiety in patients, as well as contribute to higher healthcare costs.

MRI has proven effective in selecting which patients should be sent for biopsy and which ones can be followed with active surveillance – thus avoiding biopsy’s negative consequences.

  • But what if you could eliminate biopsy altogether in some men by making the diagnosis directly with MRI, and sending patients straight to treatment? 

That’s what researchers from University College Hospital in London tried in the new EJR paper by studying 880 consecutive patients who presented to their prostate clinic and got multiparametric MRI scans. Of these, 251 were considered suspicious for disease based on their scans.

  • Radiologists interpreted the images, focusing specifically on cases where they were 99% certain that the suspected lesion was cancerous, but also grading cases at 90% and <90% certainty. Indeterminate cases could be forwarded to biopsy for further investigation.

Researchers discovered…

  • 79 patients (9% of the total) were in the “99% certain” category, with 69 going to biopsy – and 100% had clinically significant tumors.
  • 45 patients (5% of the total) were in the “90% certain” category, with 41 undergoing biopsy and 98% having clinically significant tumors.
  • The combined groups represented 14% of the patients presenting to the clinic and 49% of the suspicious cases, and only one individual did not have a clinically significant tumor.

Applying the findings to real-world clinical practice, patients in the “99% certain” or “90% certain” categories could be sent straight to prostatectomy, without the need for biopsy or PSMA-PET scans.

  • Such a straight-to-treatment protocol would be analogous to the treatment of kidney and testicular cancer, where patients are treated without biopsy on the basis of imaging scans that are definitive for cancer. 

The Takeaway

Previous studies have found that MRI can reduce biopsies in men with low suspicion of serious disease, instead directing them to active surveillance. The new research shows MRI also works at the other end of the spectrum, sparing men with clinically significant cancer the ordeal of undergoing biopsy before they can start their treatment.

VA Probes Radiologist ‘Mass Exodus’

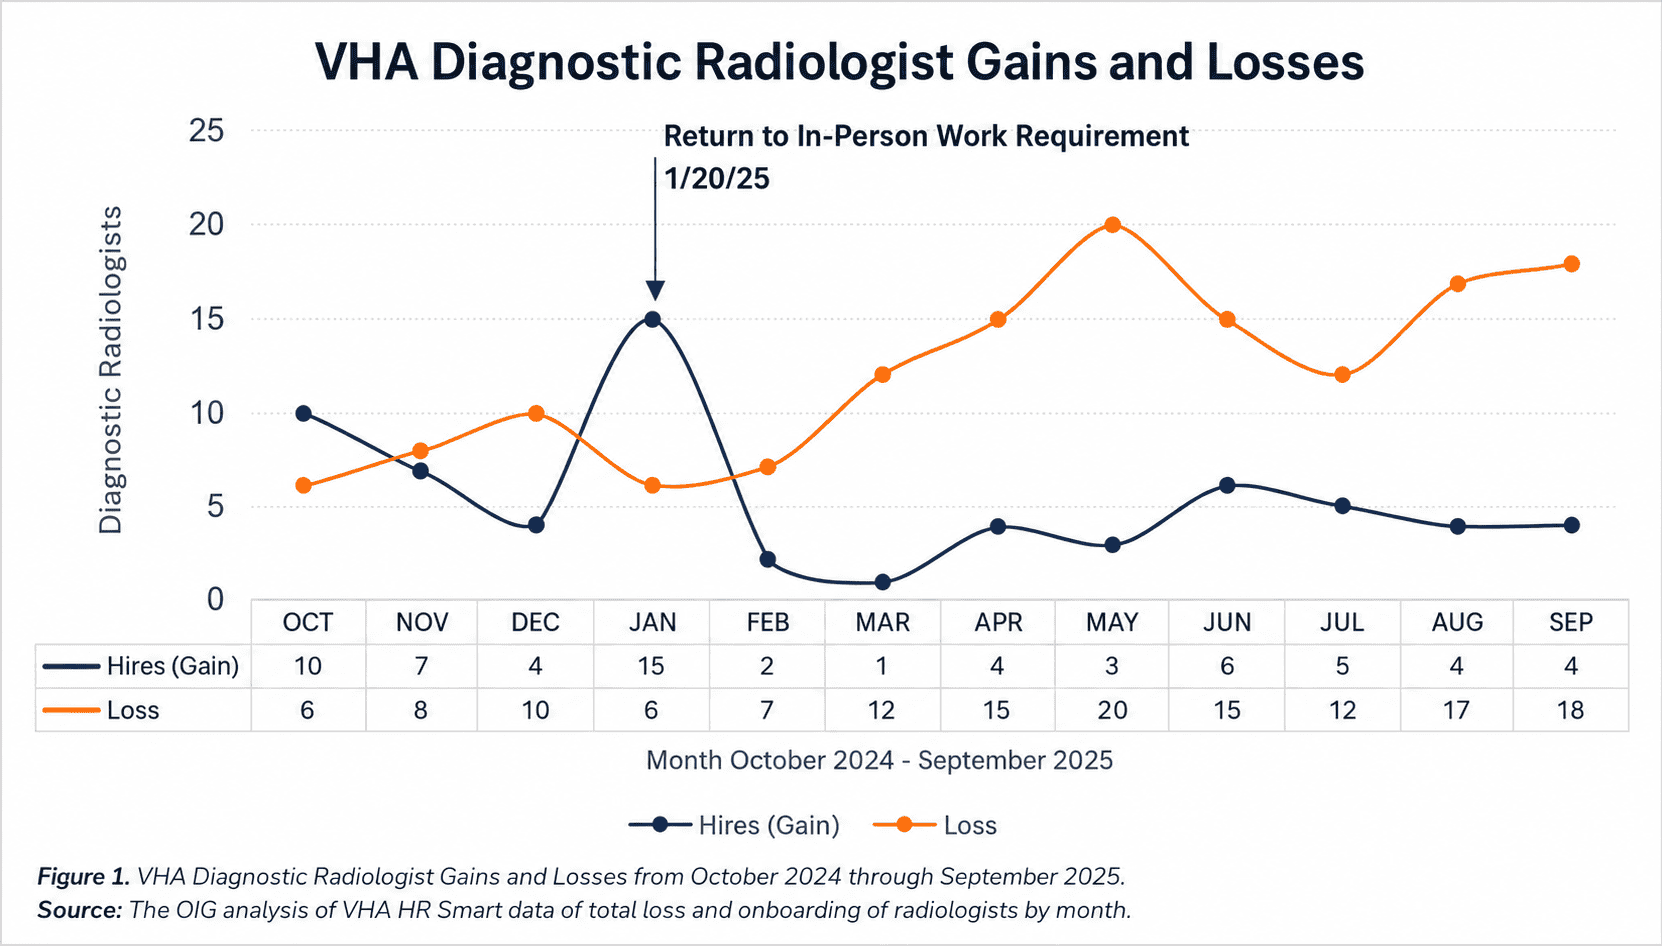
A new federal investigation confirms that a “mass exodus” of radiologists occurred at the VA hospital in Washington, DC, causing a backlog of imaging exams. The departures occurred in response to “return-to-office” requirements implemented in the early days of the second Trump administration. 

Reports began surfacing in late July of turmoil among VA radiologists that centered on the Washington DC VA Medical Center.

  • The departures were linked to changing federal policies on remote work, which has become commonplace in radiology.

The VA supported remote radiology work dating back to the COVID-19 pandemic under a policy that began as a temporary measure and subsequently “became standard practice” as radiologists were allowed to work from home several days a week. 

  • Indeed, teleradiology and remote radiology interpretations “have become factors in employment decisions for many radiologists, influencing recruitment and retention strategies across the industry,” noted a report issued in early August by the VA’s Office of Inspector General (OIG) investigating the turmoil. 

But all that changed on January 20, 2025, when a presidential memo was issued ordering heads of all federal departments and agencies to “take all necessary steps to terminate remote work arrangements and require employees to return to work in-person at their respective duty stations on a full-time basis.”

  • This sparked the departure of most of the Washington DC VA’s diagnostic radiologists, as four of the facility’s five full-time radiologists – including the chief of radiology – resigned over the next six months. 

The OIG report confirms that the return-to-office memo was a “tipping point” that “spooked” radiologists into leaving the Washington DC VA. 

  • While the VA later issued an exemption allowing remote work for radiologists, it wasn’t clear whether the exemption would be extended beyond one year, creating uncertainty and undermining the VA’s ability to recruit new radiologists. 

The turmoil has had several ramifications…

  • Body MRI scans were shut down in July 2025.
  • A backlog of CT exams developed in September 2025.
  • Imaging exams were sent out to community imaging centers.
  • The delays created the risk of patient harm, with the OIG report identifying six patient cases of particular concern.

The Takeaway

The new OIG report on radiologist departures from the VA provides a stunning look at the turmoil caused within one VA hospital by misguided government policies. The question is whether the facility’s challenges in retaining radiologists are just the tip of the iceberg, and whether similar problems extend throughout the VA health system.

CT vs. MRI for Pediatric TBI Surveillance

Sometimes less is more. That may be the case with pediatric CT for surveillance of traumatic brain injury, which should be limited as much as possible due to the radiation it delivers to young patients. Other modalities like MRI should be considered instead for follow-up.

That’s according to a new Viewpoint article in JAMA Pediatrics that proposes a new surveillance protocol relying on rapid MRI scans rather than CT to follow kids who have experienced TBI.

The authors note that the head is the most frequently imaged body region in pediatric CT, with a 2025 study claiming…

  • Cancer risk in scanned kids rose with higher radiation exposure.
  • Just two head CT scans added up to a 1.8X higher risk of hematologic malignancy by age 21.
  • 2-3 scans conferred a 2X higher brain cancer risk.

But regardless of how you interpret those statistics, few imaging specialists would dispute the need to keep pediatric CT radiation dose as low as reasonably achievable.

Instead of CT, the new imaging pathway proposed in JAMA Pediatrics recommends a rapid MRI protocol for surveillance imaging, as follows…

  • Initial TBI diagnosis should continue to be made with index cranial CT to identify hemorrhage. 
  • Stable patients should be referred to MRI using motion-tolerant and blood-sensitive sequences like T2 with gradient-echo or susceptibility-weighted imaging. 
  • Such sequences can be performed without sedation in 5-7 minutes or less.
  • For unstable patients, timely imaging – regardless of modality – and urgent neurosurgery consultation should be prioritized.  

But there are barriers to wider use of MRI, such as the availability of MRI scanners and technologists, especially outside daytime hours.

  • Nor do the authors recommend that children be transferred to other facilities solely to receive MRI scans. 

But in cases where MRI is available, every effort should be made to provide a radiation-free option for tracking children with TBI.

The Takeaway

Radiology has demonstrated impressive progress in reducing overall CT radiation dose in the long term. The new article recommending an MRI-forward pathway for following children with TBI shows that additional progress can be made when it comes to our most vulnerable patients.

CT Lung Screening Variation

Adoption of low-dose CT lung cancer screening is growing, and that’s a good thing. But rising LDCT utilization is also creating new challenges, illustrated by a new study in JACR that found high variability in radiologist interpretations. 

CT lung screening participation rates are rising, from single digits a decade ago to 19% in a recent survey. 

  • But there’s still a long way to go to get lung screening to the roughly 75% participation rate seen with breast cancer screening. 

One barrier to getting more people screened is false positives, which can cause patient anxiety and trigger a cascade of additional exams and procedures to work up suspicious findings. 

  • A major contributor to false positives may be variability in how radiologists read CT scans, so the JACR researchers investigated how interpretations for the same images changed between imaging specialists. 

Researchers looked at interpretations made by 1.4k radiologists, each of whom read a minimum of 50 LDCT screening exams (a total of 200k exams), then calculated false-positive rates for both baseline and follow-up exams. Researchers found…

  • High variability in false-positive rates, from 11% to 22%.
  • In random pairs of radiologists, on average, one radiologist would have twice the odds of making a false-positive call as the other. 
  • Radiologists with false-positive rates higher than the median rate also unsurprisingly had higher sensitivity than those below the median (97% vs. 92%).

What’s causing the variation? It could be because some radiologists use image interpretation patterns that increase false positives but also catch more cancers. 

  • In statistical terms, researchers found that for baseline screens read by radiologists who were below the median false-positive rate, they would have about 100 fewer false-positive screens for one fewer true-positive cancer. 

Radiologist variability could be reduced through programs to standardize screening interpretation, such as those implemented in mammography screening.

  • These could include support tools, automated feedback systems, educational interventions, and targeted double reading.

The Takeaway

The new findings on radiologist variability in reading CT lung cancer screening exams illustrate the delicate balance between detecting more cancer at the risk of producing additional false positives. Is the tradeoff worth it? We think we know how most patients would feel.

Rating CT Image Quality

As radiology strives to reduce CT radiation dose, one of its challenges is maintaining image quality while keeping dose low. A new five-star system for rating images is described in a new paper in EJR and could offer a solution by establishing an easy-to-understand global metric.

The radiology community has been making progress in reducing CT radiation dose, but much work remains to be done.

  • In particular, radiology professionals struggle between the desire for better-looking images – which usually result from higher radiation dose – with low-dose images that may be noisier but are good enough to make a diagnosis.

While there are lots of metrics for measuring radiation dose, image quality doesn’t have a widely recognized scale. 

  • So a team from the IAEA and MGH worked together to develop one, based on the widely recognized five-star paradigm for ranking consumer-facing businesses. 

In an interesting wrinkle, the five-star system acknowledges the dose dilemma, essentially penalizing images in which too much radiation dose was used to produce an image that’s crisper than what’s needed for diagnosis. 

  • On the other hand, the system rewards images that might be noisy due to use of less radiation, but that are still diagnostic.

 The system’s ratings are as follows…

  • Five stars – Acceptable, despite high image noise associated with low-dose CT.
  • Four stars – Acceptable for all parts within the region of interest.
  • Three stars – Acceptable, despite unintended high noise and/or some artifacts.
  • Two stars – Excellent quality with unjustifiably low image noise and no artifacts.
  • One star – Non-diagnostic, due to excessive noise or artifacts, or poor contrast.

To test the rating scale, IAEA and MGH researchers performed a study at six hospitals across five European countries. 

  • CT scans of 2.7k adults were acquired, and three radiologists per hospital were trained in the five-star scale and scored the images to see how reader subjectivity affected the scoring. 

The study found… 

  • Reader concordance was up to 93% at some sites, indicating little variability in scoring.
  • Overall discordance was rare, at 1.6%.
  • The two-star ratings (in which too much radiation was used) were associated with higher radiation dose in nearly all patient weight groups. 

The Takeaway

The new study shows that a five-star system for rating CT image quality is feasible and can reveal cases of unnecessarily high radiation dose. The question is whether the system remains an interesting thought experiment, or if it becomes an integral part of radiology’s effort to better manage radiation.

Get every issue of The Imaging Wire, delivered right to your inbox.